








Hair thinning in a woman does not automatically mean that hair transplantation is the right next step.
This is particularly important because female hair loss can be diffuse, and the scalp that appears to be a potential donor region may itself show miniaturisation.
The first question should therefore not be:
Can FUE be performed?
It should be:
What is causing the hair loss, and is there a stable donor area capable of supporting a long-term result?
Surgical literature consistently emphasises careful candidate selection, particularly because diffuse unpatterned alopecia, active scarring disorders and unstable hair loss can make transplantation inappropriate or require treatment first.
Why is female hair transplantation different?
Many men develop a relatively recognisable pattern of frontal recession, temporal loss, mid-scalp thinning and crown baldness while retaining stronger occipital and lateral donor hair.
Women often present differently.
Female Pattern Hair Loss may appear as:
Widening of the central part.
Diffuse thinning over the upper scalp.
Reduced density behind a relatively preserved frontal hairline.
In some women, thinning that also involves lateral or occipital regions.
This can make the distinction between recipient and safe donor zones less obvious.
Diagnosis comes before technique
Female hair loss can have many causes, including:
Female Pattern Hair Loss.
Telogen effluvium.
Thyroid disease.
Iron or nutritional problems.
Hormonal disorders.
Traction alopecia.
Alopecia areata.
Scarring alopecia.
Postpartum shedding.
Medication-related or inflammatory causes.
FUE does not treat the underlying cause of these conditions.
The diagnosis therefore needs to come before discussion of harvesting technique.
Who can be a good female hair-transplant candidate?
A stronger candidate typically has:
A recognised and sufficiently stable cause of hair loss.
Good donor density.
A donor region without significant diffuse miniaturisation.
A recipient area that can realistically benefit from surgery.
Reasonable expectations.
No active disease likely to damage transplanted follicles.
Women with strong occipital donor density and significant frontal or superior scalp thinning may be considered for transplantation when the condition is appropriately selected and stabilised.
Female Pattern Hair Loss
Selected women with stable FPHL may benefit from surgery.
However, donor assessment is especially important because some women also have thinning or miniaturisation in the occipital scalp.
If donor hair is weak, moving those follicles does not create a durable reserve.
Naturally high hairline
Some women have no major progressive alopecia but naturally have:
A high forehead.
A high hairline.
Temporal recession.
A shape they would like to soften.
Hair transplantation can sometimes lower or reshape the frontal frame when donor resources are suitable.
Frontotemporal recession
Women can develop noticeable frontotemporal recessions.
These areas require careful feminine hairline design rather than simply filling the corners in the same way commonly used for male-pattern recession.
Stable traction alopecia
Long-term tight hairstyles can permanently damage follicles along the margins of the scalp.
If traction has stopped and the condition is stable, transplantation may be considered in selected patients.
Stable scars
Trauma or previous surgery may leave stable areas of hair loss.
Transplantation can sometimes be used after evaluating scar quality, vascularity and the cause of the scar.
When may transplantation be unsuitable?
Diffuse Unpatterned Alopecia
DUPA affects hair density and miniaturisation outside the typical recipient area and can include the sides and back of the scalp.
Without a stable safe donor region, transplantation cannot provide a reliable long-term solution.
DUPA is therefore a major contraindication to hair transplantation.
Active alopecia areata
Alopecia areata is an immune-mediated condition.
Transplantation does not treat the underlying disease, and transplanted follicles may be affected if disease activity continues.
Active scarring alopecia
Conditions such as lichen planopilaris and other cicatricial alopecias can destroy follicles.
Operating during active disease may lead to poor growth and may potentially aggravate the inflammatory process.
Dermoscopy, trichoscopy or even biopsy can be necessary when scarring disease is suspected.
Rapidly progressive loss
When hair loss is actively accelerating, stabilisation and diagnosis generally deserve priority over immediate surgery.
What about postpartum hair loss?
Postpartum shedding is very common.
The American Academy of Dermatology describes it as excessive shedding related to falling estrogen levels after delivery rather than permanent follicular loss in most women.
Many women regain their usual fullness by their child's first birthday, often earlier.
For this reason, postpartum shedding by itself should not trigger an immediate transplant plan.
What about pregnancy?
An elective cosmetic transplant is generally not a priority during pregnancy.
Hair density and shedding patterns are also changing during pregnancy and the postpartum period, which makes long-term assessment less reliable.
Planning is more meaningful once those changes have stabilised.
Why is donor assessment so important in women?
A donor region should not simply be assumed to be permanent because it is located at the back of the head.
Female donor assessment should look for:
Density.
Miniaturisation.
Lateral thinning.
Hair calibre.
Follicular-unit composition.
Signs of inflammation or scarring.
Practice guidelines specifically emphasise examining both recipient and donor regions for diffuse thinning in female patients.
Why can trichoscopy be useful?
Early donor miniaturisation can be difficult to appreciate by visual inspection alone.
Magnification can help evaluate:
Hair-shaft diameter variation.
Miniaturisation.
Density.
Scalp abnormalities.
This helps distinguish a genuinely strong donor area from one that merely looks adequate in photographs.
What is FUE in women?
FUE stands for Follicular Unit Excision.
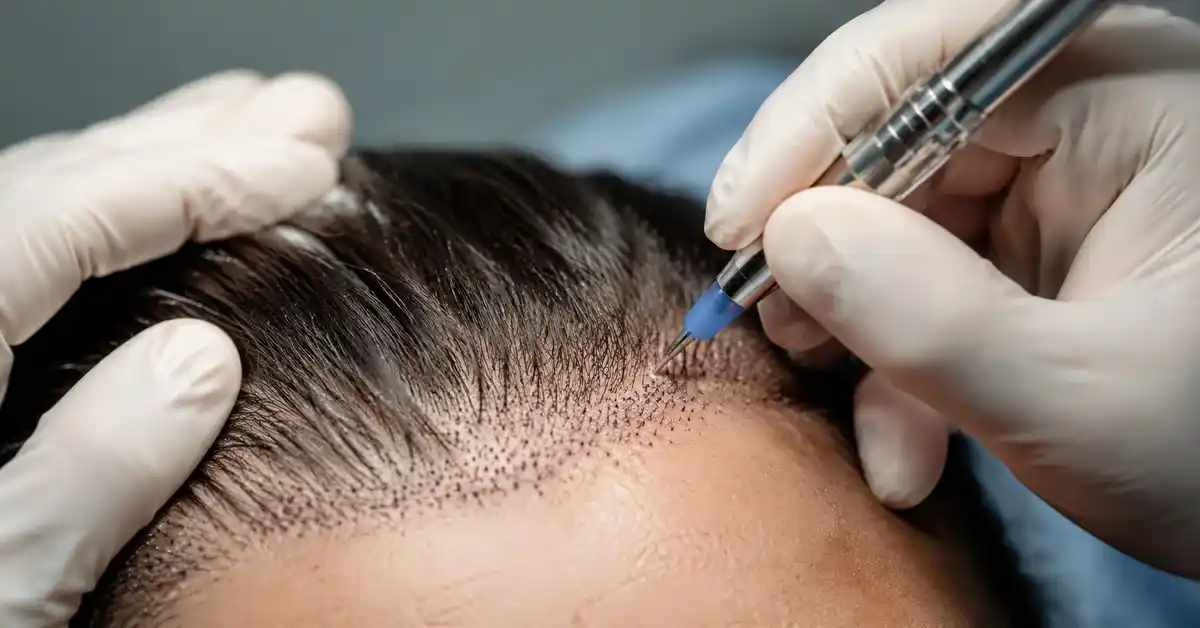
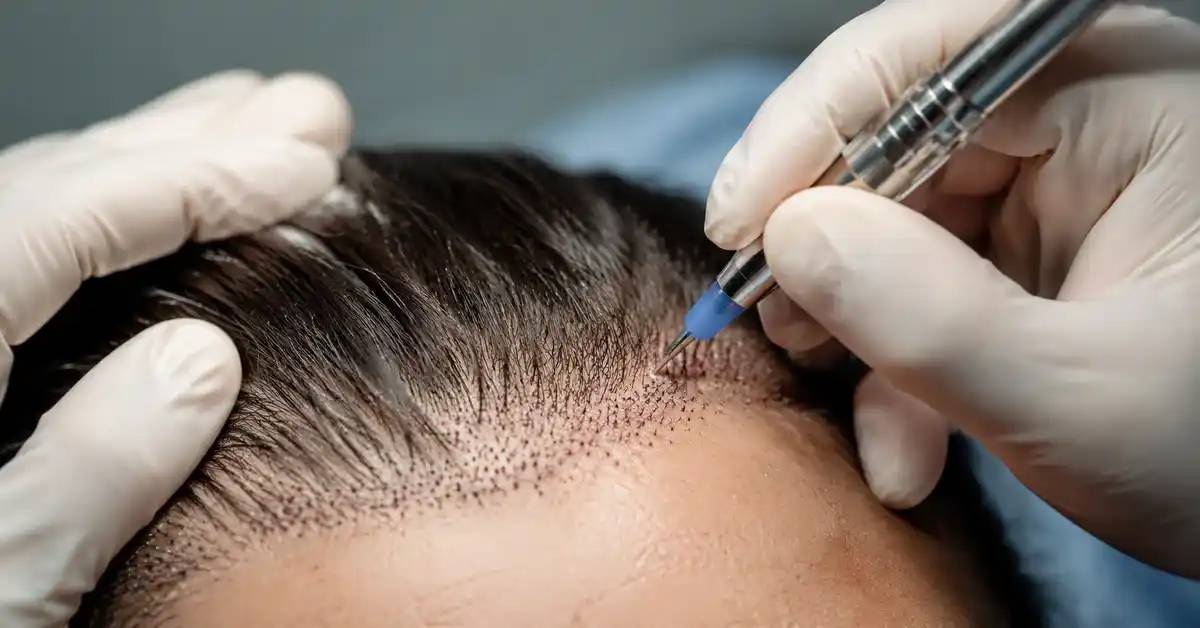
Follicular units are harvested individually through small punch incisions and then implanted into planned recipient sites.
For women, one attractive feature is avoiding a long linear donor scar.
However, FUE does not solve an unstable or diffuse donor problem.

Does all the hair need to be shaved?
Not always.
Options may include:
Shaving a concealed donor window.
Partial shaving.
Selected unshaven or long-hair approaches.
These approaches can make the procedure less visible during recovery.
However, avoiding shaving may increase procedural complexity, time and cost and may not be practical for every graft number.
Is no-shave FUE better for women?
It can be socially convenient.
It is not automatically medically superior.
The question is whether the approach allows accurate and safe harvesting for that particular case.
FUE versus FUT in women
FUE is widely used, but FUT remains a legitimate harvesting method in selected patients.
FUT removes a strip from the donor region and usually leaves a linear scar hidden under surrounding hair.
A surgeon may still discuss FUT when:
The patient wears her hair long.
Donor management favours strip harvesting.
Future donor preservation is an important consideration.
Technique should be selected for the patient rather than by gender or marketing preference.
Do women require fewer grafts?
Not necessarily.
Graft need depends on:
Recipient area.
Existing density.
Hair calibre.
Donor supply.
Treatment goals.
A woman requiring only frontal hairline lowering may need much less donor hair than a woman with broad frontal and mid-scalp thinning.
Why is transplanting between existing hairs more difficult?
Many female patients do not have completely bald scalp.
Instead, the recipient region contains existing native hairs, including miniaturised follicles.
The surgeon must:
Avoid damaging useful native follicles.
Place sites carefully between them.
Consider how much of the native hair is likely to survive long term.
This makes the procedure different from filling completely bald skin.
What is shock loss?
Native hair around the transplanted area can temporarily shed after surgery.
This is particularly important in women with substantial miniaturised native hair.
Healthy follicles often recover, but severely miniaturised hairs may not always return fully.
That possibility should be discussed during preoperative planning.
Should hair loss be treated before transplantation?
Often, yes.
When Female Pattern Hair Loss is active or diffuse, medical treatment and a period of observation may help determine whether the condition can be stabilised before surgery.
Reviews of FPHL management recommend medical therapy for suitable patients and reserve transplantation for selected cases with adequate donor hair and stable or insufficiently responsive disease.
Does treatment continue after surgery?
A transplant redistributes donor follicles.
It does not necessarily stop miniaturisation of native hair.
Women with progressive FPHL may therefore require a long-term plan to preserve the non-transplanted hair around the grafts.
How is a female hairline different?
A female hairline should not simply copy a male design.
Planning may consider:
Forehead proportions.
Facial shape.
Temporal points.
Existing hairline.
Hair direction.
Age.
A softer, more rounded contour may be appropriate in many women, with careful attention to temple framing.
Why are single-hair grafts important?
The very front of the hairline should look soft and irregular.
Single-hair follicular units are therefore valuable at the leading edge.
Larger multi-hair units can be placed farther behind to build density.
A straight wall of thick multi-hair grafts can look artificial.
Can the hairline be lowered substantially?
Sometimes.
But lowering the hairline increases recipient surface area and graft demand.
The final design needs to balance:
Facial proportions.
Donor availability.
Desired density.
Long-term maintainability.
What about temporal points?
Temporal points can strongly influence facial framing.
They also require:
Fine hairs.
Very acute implantation angles.
Precise directional control.
Poorly designed temporal points can be conspicuous, so they should not be added automatically.
Is DHI better for women?
Not universally.
DHI usually describes implantation with an implanter device.
It can be useful in selected situations, including working among native hairs, but it does not overcome:
Weak donor hair.
Incorrect diagnosis.
Active disease.
Poor long-term planning.
FUE and DHI also describe different stages of transplantation.
What about Sapphire FUE?
The material used for recipient-site blades does not independently determine success.
Diagnosis, donor management, preservation of native hair and hairline planning matter more than branding.
When does transplanted hair grow?
The basic biological timeline is similar to other scalp hair transplants.
Patients may experience:
Early shedding.
A resting phase.
New growth after several months.
Gradual thickening and maturation.
The procedure should not be judged at three or four months.
When are results visible?
New growth may begin around the third or fourth month.
Progress becomes much easier to assess around six to nine months, with further maturation toward approximately 12 months or beyond in some cases.
Why can the result change later?
Female transplants often contain a mixture of:
Transplanted follicles.
Strong native hair.
Miniaturised native hair.
If surrounding native hair continues to thin, the overall appearance may change even when transplanted grafts themselves are growing well.
That is why long-term planning matters.
Can only the part line be transplanted?
Yes, in selected cases.
But the important distinction is whether widening of the part comes from stable FPHL with good donor supply or a more diffuse process affecting the donor as well.
The recipient zone may look small but can contain many vulnerable native follicles requiring careful placement.
What if only the frontal hairline is the problem?
These can be particularly suitable cases when:
The hairline is naturally high.
There is stable frontotemporal recession.
Donor density is good.
There is no active diffuse thinning.
The surgical target can be more clearly defined than in extensive diffuse loss.
Can candidacy be assessed from photographs?
Photographs can help evaluate:
Hairline shape.
Part widening.
General thinning pattern.
Temporal recession.
General donor appearance.
But photographs cannot reliably measure:
Donor miniaturisation.
True density.
Scalp disease.
The medical cause of shedding.
Some patients therefore need in-person scalp examination, trichoscopy or additional medical evaluation.
Are blood tests always required?
No single test panel is appropriate for every woman.
Investigations should be directed by history, examination and symptoms.
Depending on the case, evaluation may look for:
Thyroid disorders.
Iron deficiency.
Hormonal abnormalities.
Hyperandrogenism.
Nutritional or systemic causes.
The purpose is targeted diagnosis, not ordering every available test.
How should you choose a clinic?
Do not ask only:
Do you perform FUE for women?
Ask:
How will you diagnose the cause of my loss?
Will you evaluate donor miniaturisation?
Who designs the hairline?
Who performs harvesting?
Who creates recipient sites?
How will you protect my existing hair?
What is my shock-loss risk?
What happens if my native hair continues thinning?
Warning signs
Be cautious if a clinic:
Recommends surgery from one photograph without discussing the diagnosis.
Treats every woman with diffuse thinning as a candidate.
Does not evaluate the donor region.
Promises a high graft number before measuring donor capacity.
Guarantees full density.
Focuses on DHI or Sapphire before discussing the cause of hair loss.
What is the biggest difference from male transplantation?
The biggest difference is not the punch.
It is case selection and planning.
Female transplantation often requires greater attention to:
Diffuse donor involvement.
Medical causes of shedding.
Preservation of native hair.
Female hairline design.
Ongoing surrounding miniaturisation.
Shock loss.
Long-term treatment of existing hair.
Conclusion
FUE hair transplantation can be an excellent option for selected women, but it is not appropriate for every type of female hair loss.
The strongest results begin with diagnosis and confirmation of a stable donor supply. Stable Female Pattern Hair Loss, naturally high hairlines, selected stable traction alopecia and stable scars may be suitable indications, while DUPA, active scarring alopecia, alopecia areata and rapidly progressive unexplained loss require caution or treatment first.
Female transplantation also requires dedicated planning of the frontal hairline, temporal regions and existing native hairs rather than simply applying a standard male transplant design.
If you are considering hair transplantation, Safemedigo can review photographs of your hairline, part line and donor region together with your available history to help determine whether the next step should be transplant assessment or further investigation and treatment of the hair loss first. Contact Safemedigo on WhatsApp.
Frequently Asked Questions
Can every woman with thinning hair undergo FUE?
No. The cause of hair loss and the stability of the donor region need to be established first.
Does a woman need to shave her whole head for FUE?
Not always. Partial or concealed shaving may be possible, depending on the procedure and graft requirement.
Is postpartum hair loss an indication for transplantation?
Usually not during the temporary shedding phase. Many women recover their normal fullness during the first year after childbirth, so the pattern should first be allowed to stabilise.
Is DHI better than FUE for women?
Not inherently. DHI usually describes implantation, while FUE describes harvesting. Diagnosis, donor quality and surgical planning are more important.
When are female hair-transplant results visible?
New growth usually begins after several months, becomes clearer around six to nine months and continues maturing toward about 12 months or longer.
