








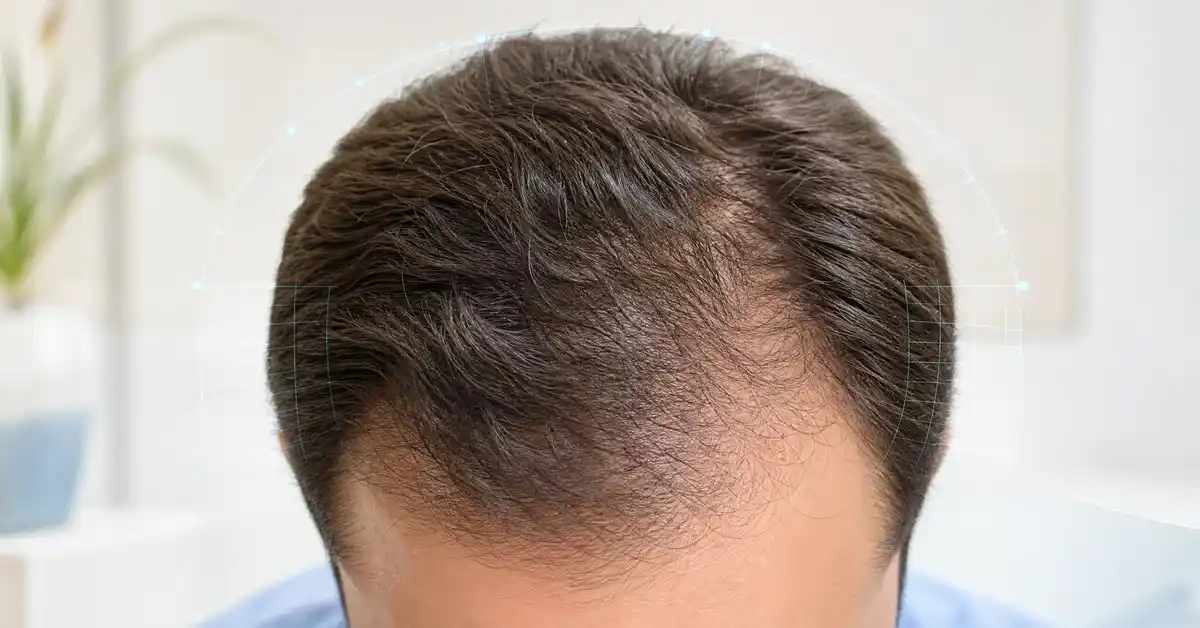
“How many grafts do I need?” is one of the most common questions asked before a hair transplant.
It is tempting to look at a Norwood chart and expect a fixed answer: Norwood III equals one number, Norwood V another.
Real surgical planning is more complex.
Two men with the same Norwood stage can require very different graft counts because they may differ in:
Recipient-area size.
Native hair density.
Hair calibre.
Hairs per follicular unit.
Hair-to-skin colour contrast.
Curl.
Donor density.
Donor miniaturisation.
Hairline design.
Crown involvement.
Future hair-loss risk.
The graft number should therefore be treated as a surgical estimate constrained by donor safety, not as a marketing target.
ISHRS practice data illustrates this variation. The 2025 census reported an average of roughly 2,347 grafts for a first procedure among responding physicians using 2024 data, but that is a practice average—not a recommendation for an individual patient.
This Safemedigo guide explains what a graft means, how graft requirements are estimated and why more grafts are not automatically better.
What exactly is a graft?
A follicular-unit graft is not necessarily one hair.
A naturally occurring follicular unit may contain:
One hair.
Two hairs.
Three hairs.
Occasionally more.
Therefore:
3,000 grafts does not mean 3,000 hairs.
The actual number of transplanted hairs can be substantially higher.
Why does this distinction matter?
Some clinics advertise “hairs” while others quote “grafts.”
For example:
5,000 hairs
and
5,000 grafts
are very different claims.
Before comparing quotations, ask:
Is this number follicular-unit grafts or individual hairs?
What determines graft requirements?
Three questions form the core of planning:
How large is the recipient area?
What density is appropriate for each zone?
How many grafts can the donor safely provide?
The third question places the ceiling on the plan.
A patient may theoretically need more hair than the donor area can safely supply.
Measuring the recipient area
Norwood stage alone cannot accurately measure surgical demand.
The scalp is better considered as separate treatment zones:
Hairline.
Frontal zone.
Mid-scalp.
Crown or vertex.
Each area can be estimated in square centimetres.
A simplified planning formula is:
recipient area in cm² × planned follicular-unit density = approximate graft requirement
However, planned density is not identical across the entire scalp.
Should every area receive the same density?
No.
The frontal region usually deserves greater visual priority because it frames the face.
The crown can consume a very large donor supply if surgeons attempt to reproduce high density over its full surface area.
Published planning approaches commonly use a stronger density gradient anteriorly and lower density toward the crown rather than applying one uniform number across the scalp.
Hairline reconstruction
A patient who only needs temple or hairline restoration may require far fewer grafts than someone whose entire frontal third is bald.
Factors include:
Forehead width.
Degree of recession.
Proposed hairline height.
Temple design.
Existing density behind the hairline.
The leading edge also requires a large proportion of single-hair grafts for natural softness.
Frontal zone
The frontal third has a major impact on appearance.
When donor supply is limited, many treatment plans prioritise this area.
Graft need depends on:
Surface area.
Existing native hair.
Miniaturisation.
Hair calibre.
Desired visual density.
Mid-scalp
The mid-scalp may be completely bald or contain substantial miniaturised native hair.
Those are very different situations.
A thinning zone with salvageable native hair may not require the same graft density as completely bare scalp.
Crown
The crown can be exceptionally graft-hungry.
Reasons include:
Large surface area.
Spiral growth pattern.
Visibility from multiple directions.
The need to recreate a whorl rather than a straight flow pattern.
In advanced baldness, the surgeon may deliberately use lower crown density or defer part of the crown to preserve donor reserves.
Practical planning by zone
| Zone | Main factors affecting graft requirement |
|---|---|
| Hairline | Width, recession, design, single-hair graft requirement |
| Frontal zone | Area, existing hair and desired visual density |
| Mid-scalp | Thinning area and remaining miniaturised hair |
| Crown | Surface area, whorl pattern and priority |
| Multiple zones | Donor capacity and allocation between zones |
| Advanced baldness | Lifetime donor supply and staged planning |
This is more useful than treating every Norwood stage as one fixed graft number.
Is there an ideal grafts-per-cm² density?
There is no universal ideal density.
Planning depends on:
Hair calibre.
Hairs per graft.
Recipient zone.
Blood supply.
Native hair.
Surface area.
Donor reserve.
Some published practice frameworks use higher follicular-unit densities in the frontal core and lower targets through the mid-scalp and crown, but these are planning conventions rather than universal prescriptions.
Why not recreate full native density?
Natural scalp density can be much higher than the density that can safely or realistically be recreated across a large bald area.
Hair restoration aims to create the appearance of density using a limited donor supply.
A thick, wavy hair shaft can produce substantially better coverage than fine straight hair using the same graft count.
Hair calibre matters
Consider two patients with 3,000 grafts.
Patient A
Thick, wavy hair.
Patient B
Fine, straight hair.
Patient A may achieve much stronger visual coverage despite receiving the same graft number.
This is why comparing clinics solely by graft count is misleading.
Hair and skin colour contrast
Lower contrast between hair and scalp can create a fuller visual effect.
High contrast can make scalp visibility more noticeable.
This can influence how much visual density is needed.
Curl changes visual coverage
Curly and wavy hairs occupy more visual space.
This can improve coverage, but it is only one factor among many and should not be used as a simple formula for reducing graft numbers.
Hairs per follicular unit
Two donor areas with identical follicular-unit density may not provide the same cosmetic value.
A donor with many multi-hair units can provide stronger coverage than one dominated by single-hair units.
Therefore donor evaluation should consider both:
follicular units per cm²
and
average hairs per follicular unit.
Is the Norwood Scale useful?
Yes—but it is not a graft calculator.
Norwood classification describes male-pattern hair-loss patterns.
It does not measure:
Actual scalp surface area.
Donor density.
Hair calibre.
Follicular-unit composition.
Patient age.
Remaining miniaturised hair.
Two Norwood V patients can therefore require very different plans.

Can you use a Norwood-to-graft table?
Only as a broad educational reference.
The danger is treating the table as a surgical target regardless of donor capacity.
A stronger method begins with:
area + planned density + donor capacity.
How many grafts can the donor provide?
There is no universal number.
Safe capacity depends on:
Safe donor-zone size.
Follicular-unit density.
Hair calibre.
Miniaturisation.
Retrograde alopecia.
Previous procedures.
Age.
Expected future loss.
The donor is a limited lifetime resource.
Why not harvest the maximum possible number?
Because excessive extraction can create:
Visible donor thinning.
Patchiness.
A moth-eaten appearance.
Reduced options for future surgery.
Modern donor-management approaches emphasise preserving lifetime reserves instead of maximising one session.
Is 4,000 grafts better than 3,000?
Not necessarily.
A 3,000-graft plan may be superior if it:
Prioritises the right areas.
Produces better distribution.
Protects the donor.
Anticipates future loss.
Graft count is not a quality score.
Is “maximum grafts” a good selling point?
It should prompt questions.
If a clinic promises:
the maximum possible number
before properly assessing donor density and future hair loss, the plan may be driven by quantity rather than strategy.
The goal is not the largest number that can physically be extracted.
It is the number that is needed and safely available.
Why might a surgeon recommend fewer grafts than the patient wants?
Long-term planning.
For example, a 25-year-old with frontal recession may later progress to extensive baldness.
Using a very low hairline and aggressive graft count now can create problems when the mid-scalp and crown thin later.
Does age affect graft planning?
Yes, indirectly.
Age does not dictate graft count, but younger patients may require more conservative planning when their final pattern of hair loss is not yet clear.
Why are some treatments divided into two sessions?
Trying to restore a very large bald area in one procedure is not always optimal.
A staged approach might involve:
Session 1
Hairline, frontal scalp and perhaps mid-scalp.
Session 2
Additional density or crown restoration after the first result has matured.
Staging can be deliberate donor management rather than a sign of failure.
Is one session always enough?
No.
ISHRS practice data suggests many patients may reach their desired goal with one procedure, while others require further treatment, reflecting differences in extent of loss and treatment objectives.
Can graft number be estimated from photographs?
Photographs can provide a useful preliminary range.
They help show:
Hair-loss pattern.
Treatment zones.
Existing hairline.
Crown involvement.
General donor appearance.
However, photographs cannot accurately measure:
Curved scalp surface area.
True donor density.
Miniaturisation.
Hair calibre.
Hairs per follicular unit.
The final plan is more reliable after direct examination or detailed donor assessment.
Why can photographs underestimate area?
The scalp is curved.
A two-dimensional photograph can distort surface area depending on the angle.
Direct zone measurement on the scalp can therefore produce a more defensible estimate than photographs alone.
Are online graft calculators accurate?
They can be educational.
They should not determine surgery.
If an online calculator produces a precise answer such as:
3,427 grafts
that does not mean your scalp literally requires that exact count.
How does graft count affect price?
Some clinics price per graft.
Others use fixed procedure or package pricing.
Pricing structure should not determine the medical graft plan.
The surgeon should not harvest additional grafts simply because the commercial model rewards a larger number.
Does DHI require fewer grafts than FUE?
Not as a general rule.
FUE primarily describes follicular harvesting.
DHI commonly describes implantation using an implanter.
Recipient area and donor capacity determine graft need—not the marketing name of the implantation method.
Does Sapphire change the graft requirement?
No universal rule supports that.
The number required comes from recipient planning, not the material used for recipient-site blades.
Does robotic FUE reduce the number needed?
No.
Robotics can assist selected harvesting or planning tasks, but it cannot reduce the size of the bald area or manufacture additional donor follicles.
What about partial baldness?
Partial loss may require fewer grafts because native hair remains.
However, miniaturisation and future progression must still be considered.
What if only the crown needs treatment?
A crown-only procedure can be planned when the frontal region remains strong.
However, patients should understand that the crown can consume a large donor supply.
The value of dense crown restoration must therefore be weighed against the possibility of future frontal or mid-scalp loss.
What about Norwood VI or VII?
In advanced baldness, theoretical demand may exceed safe donor supply.
The useful question becomes:
How should the available grafts be distributed for the strongest cosmetic effect?
A plan may involve:
A conservative hairline.
Frontal priority.
Lower density over wider zones.
More than one session.
Limited crown restoration.
Can beard hair increase donor supply?
In selected patients, beard or other body hair may supplement scalp grafts.
However, these hairs differ in:
Calibre.
Texture.
Growth cycle.
Cosmetic behaviour.
They should not be used to justify excessively aggressive scalp harvesting.
How can you judge whether a graft quote is reasonable?
Ask:
What area are you planning to cover?
What density is planned for each zone?
How was my donor density assessed?
Is there donor miniaturisation?
How much donor reserve will remain?
Why was this graft number selected?
What happens if my hair loss progresses?
Are you quoting grafts or individual hairs?
A statement such as:
“We can take 5,000 grafts”
without the reasoning behind it is not enough.
A practical example
Imagine a patient with:
Receded hairline.
Frontal thinning.
Mild crown thinning with substantial native hair remaining.
A sensible plan might prioritise:
Strong frontal framing.
Moderate density behind it.
Medical management or observation of the crown.
Another patient with the same Norwood classification but an almost bald crown would require a very different allocation.
This is why a single chart cannot plan every patient.
What should a good treatment proposal include?
Ideally:
Treatment zones.
Expected graft range.
Rationale.
Donor assessment.
Future-loss considerations.
Possible staged treatment.
Technique and why it is being recommended.
Conclusion
The number of grafts required for a hair transplant cannot be determined reliably from Norwood stage alone or from a fixed chart found online.
A sound estimate combines recipient-area size, target density, hair calibre, hairs per follicular unit, remaining native hair and long-term design.
But even when a bald area could theoretically use a very large number of grafts, one question remains decisive:
How many grafts can the donor safely provide without creating visible depletion or sacrificing future options?
That is why a carefully planned 3,000-graft procedure may be better than an aggressive 4,500-graft session, and why staged treatment can be smarter than trying to cover everything at once.
If you want an initial estimate of your graft requirement, Safemedigo can review photographs of your hairline, frontal scalp, mid-scalp, crown and donor region before a more precise medical assessment confirms the treatment plan. Contact Safemedigo on WhatsApp.
Frequently Asked Questions
How many grafts do I need for a hair transplant?
There is no fixed number. It depends on recipient area, desired density, hair characteristics, donor capacity and long-term hair-loss planning.
Are 4,000 grafts better than 3,000?
Not necessarily. Safe donor preservation and intelligent graft distribution matter more than simply using the largest number.
Can graft numbers be estimated from photographs?
A preliminary range can often be estimated, but accurate planning also requires donor density, miniaturisation, hair calibre and recipient-area assessment.
Does the Norwood Scale determine graft count?
No. It describes the pattern of hair loss but does not account for scalp size, donor density, hair characteristics or remaining native hair.
Can all required grafts be transplanted in one session?
Not always. Extensive baldness or limited donor capacity may make staged treatment safer and more strategically effective.
